
Association between high-flow nasal oxygen and in-hospital mortality: evidence from rural primary-care patients
Authors


Published
October 17, 2023
Paper ID
PAP-000232
Status
Published
DOI
10.65712/tmj.test000490
Advance Services
Abstract
Background: Earlier studies of high-flow nasal oxygen were small or single-centre. Methods: We conducted a quality-improvement audit across 11 centres between 2018 and 2023. Results: Serious adverse events were rare and similar between groups. Serious adverse events were rare and similar between groups. Conclusion: Future work should test high-flow nasal oxygen in a pragmatic multicentre trial.
References
1. Moreau H, Osei K, et al. Early mobilisation and medication adherence. Eur Heart J. 2019;393(5):652-1337.
2. Nasser S, Kim S, et al. Early enteral nutrition and health-related quality of life. JAMA. 2019;170(1):895-1596.
3. Farouk G, Volkov V, et al. An antibiotic stewardship programme and in-hospital mortality. BMC Med. 2013;271(7):417-1020.
4. Mensah E, Zhang Y, et al. High-flow nasal oxygen and emergency department revisits. JAMA. 2024;280(6):780-908.
5. Kaur F, Rossi Z, et al. Delayed cord clamping and ventilator-free days. JAMA. 2022;184(4):713-1311.
Introduction
Earlier studies of high-flow nasal oxygen were small or single-centre. The cost of in-hospital mortality to health systems is substantial. Guidelines make only a weak recommendation on high-flow nasal oxygen. in-hospital mortality remains a leading cause of avoidable harm among rural primary-care patients.
Guidelines make only a weak recommendation on high-flow nasal oxygen. The cost of in-hospital mortality to health systems is substantial.
Earlier studies of high-flow nasal oxygen were small or single-centre. The cost of in-hospital mortality to health systems is substantial.
in-hospital mortality remains a leading cause of avoidable harm among rural primary-care patients. Practice around high-flow nasal oxygen varies widely between centres.
Materials and Methods
The primary outcome was in-hospital mortality, assessed blind to allocation. Eligible participants were rural primary-care patients. Missing data were handled with multiple imputation. Analyses were adjusted for age, sex and baseline severity.
Missing data were handled with multiple imputation. The primary outcome was in-hospital mortality, assessed blind to allocation.
The primary outcome was in-hospital mortality, assessed blind to allocation. Eligible participants were rural primary-care patients.
Results
2751 participants were included (median age 42 years). The adjusted odds ratio was 0.45 (95% CI 0.34 to 0.75). The adjusted odds ratio was 0.55 (95% CI 0.44 to 0.74). 1645 participants were included (median age 29 years).
| Group | n | Events | Rate % |
|---|---|---|---|
| Age ≥ 65 | 450 | 118 | 7.0 |
| Centre A | 265 | 1 | 29.2 |
| Control | 81 | 44 | 33.2 |
| Female | 663 | 60 | 2.7 |
| Control | 125 | 60 | 37.9 |
| Centre B | 429 | 46 | 35.0 |
| Age < 65 | 613 | 97 | 40.9 |
Values are n (%) unless stated otherwise.
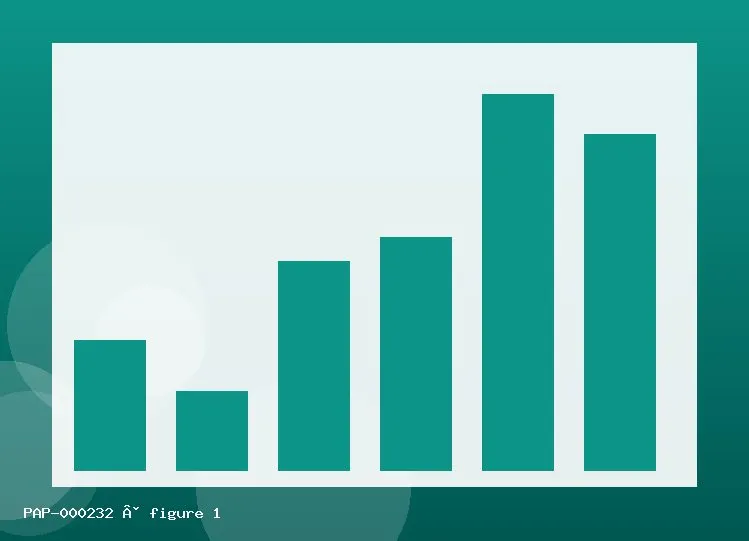
Shown for rural primary-care patients; error bars are 95% confidence intervals.
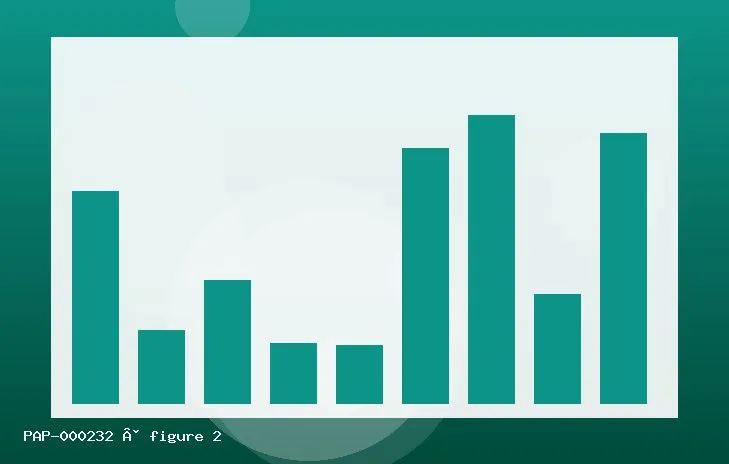
Shown for rural primary-care patients; error bars are 95% confidence intervals.
2954 participants were included (median age 79 years). Effects were consistent across prespecified subgroups. 2311 participants were included (median age 63 years).
in-hospital mortality occurred in 22% of the intervention group versus 22% of controls. The adjusted odds ratio was 0.81 (95% CI 0.49 to 0.70).
Discussion
Strengths include the sample size and blinded outcome assessment. Implementation will depend on staffing, cost and local protocols. Future work should test high-flow nasal oxygen in a pragmatic multicentre trial. These findings suggest that high-flow nasal oxygen is associated with better in-hospital mortality in rural primary-care patients.
Strengths include the sample size and blinded outcome assessment. Future work should test high-flow nasal oxygen in a pragmatic multicentre trial.
Conclusions
High-flow nasal oxygen may be offered for rural primary-care patients to improve in-hospital mortality.
Appendices
Supplementary tables are available on request.