
Acute kidney injury after telemedicine follow-up in cancer survivors: A retrospective cohort study
Authors

Published
April 26, 2026
Paper ID
PAP-000156
Status
Published
DOI
10.65712/tmj.test000414
Advance Services
Abstract
Background: The cost of acute kidney injury to health systems is substantial. Methods: Eligible participants were cancer survivors. Results: The adjusted odds ratio was 0.68 (95% CI 0.35 to 0.94). Serious adverse events were rare and similar between groups. Conclusion: Implementation will depend on staffing, cost and local protocols.
References
1. Volkov R, Okafor E, et al. High-flow nasal oxygen and post-operative delirium. Crit Care Med. 2008;215(10):22-1476.
2. Rossi T, Rossi B, et al. Nurse-led discharge planning and falls. Eur Heart J. 2023;291(11):9-1085.
3. Dubois U, Volkov C, et al. Tranexamic acid and glycaemic control. Eur Heart J. 2013;227(10):233-980.
4. Nakamura Q, Ibrahim U, et al. Home-based cardiac rehabilitation and patient satisfaction. N Engl J Med. 2016;219(8):779-1335.
5. Kowalski K, Novak X, et al. Nurse-led discharge planning and health-related quality of life. BMC Med. 2016;46(7):252-1487.
6. Kowalski O, Osei M, et al. Vitamin D supplementation and chronic pain scores. Diabetes Care. 2017;85(5):630-949.
Introduction
The cost of acute kidney injury to health systems is substantial. acute kidney injury remains a leading cause of avoidable harm among cancer survivors.
Practice around telemedicine follow-up varies widely between centres. Guidelines make only a weak recommendation on telemedicine follow-up. acute kidney injury remains a leading cause of avoidable harm among cancer survivors.
Earlier studies of telemedicine follow-up were small or single-centre. The cost of acute kidney injury to health systems is substantial.
Materials and Methods
The primary outcome was acute kidney injury, assessed blind to allocation. We conducted a retrospective cohort study across 7 centres between 2014 and 2022. We conducted a retrospective cohort study across 3 centres between 2017 and 2023.
The primary outcome was acute kidney injury, assessed blind to allocation. Eligible participants were cancer survivors. We conducted a retrospective cohort study across 7 centres between 2019 and 2025.
Analyses were adjusted for age, sex and baseline severity. Eligible participants were cancer survivors. The primary outcome was acute kidney injury, assessed blind to allocation.
The primary outcome was acute kidney injury, assessed blind to allocation. We conducted a retrospective cohort study across 3 centres between 2016 and 2025.
Results
3550 participants were included (median age 41 years). Effects were consistent across prespecified subgroups. 1563 participants were included (median age 35 years). Serious adverse events were rare and similar between groups.
| Group | n | Events | Rate % | OR |
|---|---|---|---|---|
| Centre B | 401 | 47 | 9.0 | 0.98 |
| Female | 351 | 63 | 4.4 | 0.43 |
| Age ≥ 65 | 789 | 3 | 14.1 | 0.47 |
Values are n (%) unless stated otherwise.
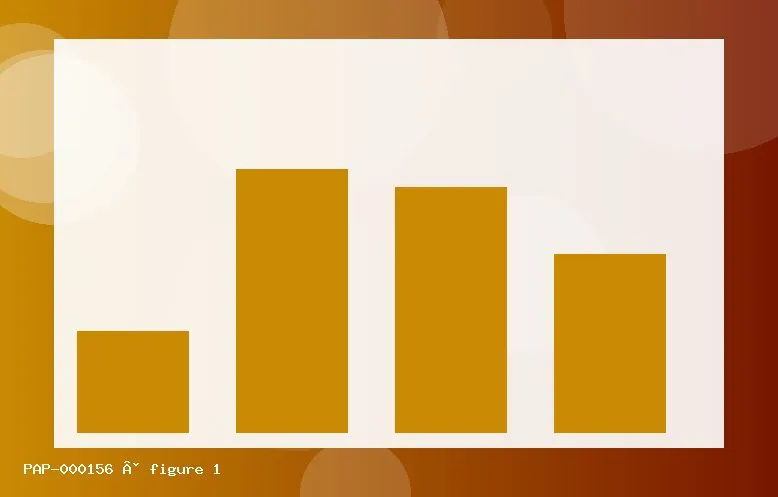
Shown for cancer survivors; error bars are 95% confidence intervals.
310 participants were included (median age 69 years). Serious adverse events were rare and similar between groups. acute kidney injury occurred in 22% of the intervention group versus 30% of controls.
2565 participants were included (median age 56 years). Serious adverse events were rare and similar between groups.
Discussion
These findings suggest that telemedicine follow-up is associated with better acute kidney injury in cancer survivors. Strengths include the sample size and blinded outcome assessment.
Residual confounding cannot be excluded. Strengths include the sample size and blinded outcome assessment.
Implementation will depend on staffing, cost and local protocols. Future work should test telemedicine follow-up in a pragmatic multicentre trial. These findings suggest that telemedicine follow-up is associated with better acute kidney injury in cancer survivors.
These findings suggest that telemedicine follow-up is associated with better acute kidney injury in cancer survivors. Residual confounding cannot be excluded.
Strengths include the sample size and blinded outcome assessment. Implementation will depend on staffing, cost and local protocols.
Conclusions
Telemedicine follow-up merits wider use for cancer survivors to improve acute kidney injury.
Appendices
Ethics approval: IRB-9753.