
Prone positioning and health-related quality of life in pregnant women: A randomised controlled trial
Authors

Published
September 16, 2026
Paper ID
PAP-000109
Status
Published
DOI
10.65712/tmj.test000367
Advance Services
Abstract
Background: Practice around prone positioning varies widely between centres. Methods: Missing data were handled with multiple imputation. Results: 4683 participants were included (median age 31 years). 2309 participants were included (median age 37 years). Conclusion: Future work should test prone positioning in a pragmatic multicentre trial.
Introduction
health-related quality of life remains a leading cause of avoidable harm among pregnant women. Guidelines make only a weak recommendation on prone positioning. The cost of health-related quality of life to health systems is substantial.
Earlier studies of prone positioning were small or single-centre. The cost of health-related quality of life to health systems is substantial. health-related quality of life remains a leading cause of avoidable harm among pregnant women. Guidelines make only a weak recommendation on prone positioning.
Guidelines make only a weak recommendation on prone positioning. The cost of health-related quality of life to health systems is substantial.
Discussion
Residual confounding cannot be excluded. These findings suggest that prone positioning is associated with better health-related quality of life in pregnant women. Strengths include the sample size and blinded outcome assessment.
Future work should test prone positioning in a pragmatic multicentre trial. Strengths include the sample size and blinded outcome assessment.
Conclusions
Prone positioning may be offered for pregnant women to improve health-related quality of life.
References
1. Haddad F, Tanaka V, et al. Telemedicine follow-up and 30-day readmission. Diabetes Care. 2020;169(3):849-1102.
2. Osei E, Zhang Y, et al. Continuous glucose monitoring and emergency department revisits. JAMA. 2012;396(7):363-1635.
3. Haddad S, Ahmed F, et al. Home-based cardiac rehabilitation and emergency department revisits. Pediatrics. 2020;144(7):5-1751.
4. Kim A, Novak P, et al. Point-of-care ultrasound and length of stay. Eur Heart J. 2013;180(7):668-1686.
5. Larsen Z, Volkov I, et al. A sepsis alert system and chronic pain scores. N Engl J Med. 2025;365(7):500-1254.
6. Yilmaz J, Kim F, et al. Delayed cord clamping and length of stay. Pediatrics. 2010;159(11):224-1723.
7. Mensah I, Novak A, et al. Home-based cardiac rehabilitation and ventilator-free days. BMJ. 2018;234(1):329-1645.
Appendices
The statistical analysis plan is in the online supplement.
Materials and Methods
Eligible participants were pregnant women. Analyses were adjusted for age, sex and baseline severity. We conducted a randomised controlled trial across 12 centres between 2019 and 2022. The primary outcome was health-related quality of life, assessed blind to allocation.
Eligible participants were pregnant women. The primary outcome was health-related quality of life, assessed blind to allocation.
We conducted a randomised controlled trial across 10 centres between 2014 and 2021. Analyses were adjusted for age, sex and baseline severity.
We conducted a randomised controlled trial across 2 centres between 2019 and 2023. We conducted a randomised controlled trial across 5 centres between 2016 and 2025.
Results
The adjusted odds ratio was 0.71 (95% CI 0.30 to 0.83). The adjusted odds ratio was 0.65 (95% CI 0.35 to 0.79).
Serious adverse events were rare and similar between groups. health-related quality of life occurred in 11% of the intervention group versus 14% of controls.
| Group | n | Events | Rate % | OR | 95% CI |
|---|---|---|---|---|---|
| Intervention | 74 | 71 | 13.5 | 0.81 | 0.52–1.11 |
| Intervention | 97 | 51 | 22.0 | 0.98 | 0.36–1.18 |
| Control | 684 | 108 | 37.1 | 0.69 | 0.52–1.35 |
| Age < 65 | 711 | 67 | 22.3 | 0.77 | 0.44–1.25 |
Values are n (%) unless stated otherwise.
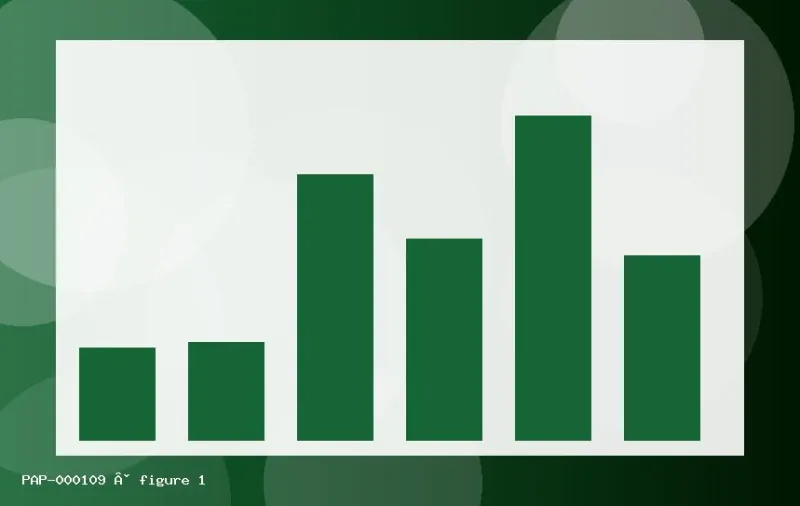
Shown for pregnant women; error bars are 95% confidence intervals.
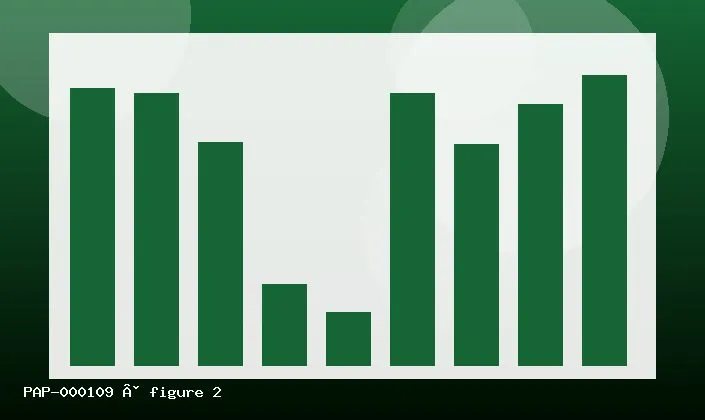
Shown for pregnant women; error bars are 95% confidence intervals.
362 participants were included (median age 45 years). Serious adverse events were rare and similar between groups.
health-related quality of life occurred in 18% of the intervention group versus 36% of controls. Serious adverse events were rare and similar between groups. 589 participants were included (median age 79 years).