
A sepsis alert system and post-operative delirium in preterm neonates: A randomised controlled trial
Authors


Published
March 12, 2024
Paper ID
PAP-000271
Status
Published
DOI
10.65712/tmj.test000529
Advance Services
Abstract
Background: post-operative delirium remains a leading cause of avoidable harm among preterm neonates. Methods: Eligible participants were preterm neonates. Results: 4570 participants were included (median age 35 years). Serious adverse events were rare and similar between groups. Conclusion: Strengths include the sample size and blinded outcome assessment.
Introduction
Earlier studies of a sepsis alert system were small or single-centre. Practice around a sepsis alert system varies widely between centres.
Guidelines make only a weak recommendation on a sepsis alert system. The cost of post-operative delirium to health systems is substantial.
Guidelines make only a weak recommendation on a sepsis alert system. Earlier studies of a sepsis alert system were small or single-centre.
Guidelines make only a weak recommendation on a sepsis alert system. The cost of post-operative delirium to health systems is substantial.
Discussion
Residual confounding cannot be excluded. Strengths include the sample size and blinded outcome assessment.
Future work should test a sepsis alert system in a pragmatic multicentre trial. Residual confounding cannot be excluded. Implementation will depend on staffing, cost and local protocols.
Conclusions
A sepsis alert system is a reasonable option for preterm neonates to improve post-operative delirium.
References
1. Ibrahim K, Farouk E, et al. Telemedicine follow-up and post-operative delirium. Pediatrics. 2019;343(5):278-1769.
2. Nasser F, Mueller O, et al. Delayed cord clamping and falls. Pediatrics. 2011;251(2):23-1213.
3. Lindqvist V, Kaur V, et al. An enhanced recovery pathway and time to diagnosis. Lancet. 2011;287(5):692-1459.
4. Rahman T, Ibrahim U, et al. An enhanced recovery pathway and post-operative delirium. Pediatrics. 2025;12(7):158-1321.
5. Dubois O, Schmidt F, et al. Nurse-led discharge planning and falls. N Engl J Med. 2011;306(9):181-1221.
6. Nakamura G, Rahman W, et al. Telemedicine follow-up and 30-day readmission. Eur Heart J. 2014;290(1):615-1166.
Appendices
Ethics approval: IRB-7154.
Materials and Methods
Eligible participants were preterm neonates.
The primary outcome was post-operative delirium, assessed blind to allocation. Analyses were adjusted for age, sex and baseline severity.
We conducted a randomised controlled trial across 6 centres between 2017 and 2025. Missing data were handled with multiple imputation. Analyses were adjusted for age, sex and baseline severity. The primary outcome was post-operative delirium, assessed blind to allocation.
Results
The adjusted odds ratio was 0.80 (95% CI 0.27 to 0.77). post-operative delirium occurred in 6% of the intervention group versus 14% of controls. The adjusted odds ratio was 0.86 (95% CI 0.38 to 0.70).
The adjusted odds ratio was 0.48 (95% CI 0.46 to 0.74). Serious adverse events were rare and similar between groups. 4117 participants were included (median age 28 years). 1658 participants were included (median age 41 years).
| Group | n | Events | Rate % |
|---|---|---|---|
| Centre A | 530 | 39 | 18.4 |
| Control | 838 | 70 | 20.9 |
| Centre B | 818 | 59 | 20.1 |
| Female | 25 | 93 | 4.0 |
| Intervention | 285 | 4 | 38.0 |
| Age < 65 | 659 | 103 | 19.9 |
| Intervention | 113 | 78 | 1.2 |
Values are n (%) unless stated otherwise.
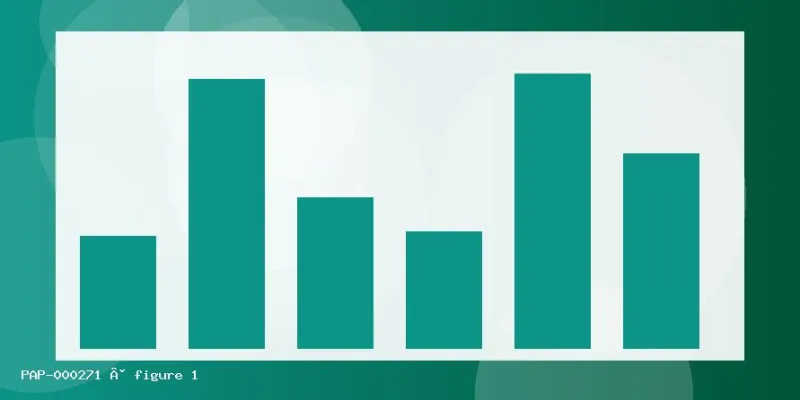
Shown for preterm neonates; error bars are 95% confidence intervals.
post-operative delirium occurred in 17% of the intervention group versus 22% of controls. Serious adverse events were rare and similar between groups.
The adjusted odds ratio was 0.60 (95% CI 0.50 to 0.67). Serious adverse events were rare and similar between groups. 2196 participants were included (median age 45 years). The adjusted odds ratio was 0.55 (95% CI 0.30 to 0.60).