
Rethinking medication adherence in adults with type 2 diabetes: the role of early enteral nutrition
Authors


Published
August 13, 2024
Paper ID
PAP-000179
Status
Published
DOI
10.65712/tmj.test000437
Advance Services
Abstract
Background: Guidelines make only a weak recommendation on early enteral nutrition. Methods: The primary outcome was medication adherence, assessed blind to allocation. Results: medication adherence occurred in 12% of the intervention group versus 21% of controls. Effects were consistent across prespecified subgroups. Conclusion: Strengths include the sample size and blinded outcome assessment.
Introduction
medication adherence remains a leading cause of avoidable harm among adults with type 2 diabetes. Guidelines make only a weak recommendation on early enteral nutrition.
The cost of medication adherence to health systems is substantial. Practice around early enteral nutrition varies widely between centres.
medication adherence remains a leading cause of avoidable harm among adults with type 2 diabetes.
Earlier studies of early enteral nutrition were small or single-centre. medication adherence remains a leading cause of avoidable harm among adults with type 2 diabetes.
Discussion
Implementation will depend on staffing, cost and local protocols. These findings suggest that early enteral nutrition is associated with better medication adherence in adults with type 2 diabetes.
Strengths include the sample size and blinded outcome assessment. Residual confounding cannot be excluded.
Conclusions
Early enteral nutrition is a reasonable option for adults with type 2 diabetes to improve medication adherence.
References
1. Kaur Z, Moreau C, et al. Early enteral nutrition and medication adherence. BMJ. 2024;87(10):240-1343.
2. Yilmaz S, Costa I, et al. Vitamin D supplementation and acute kidney injury. BMJ. 2019;225(4):67-1480.
3. Zhang J, Tanaka M, et al. SGLT2 inhibitors and health-related quality of life. Lancet. 2021;373(7):453-1314.
4. Larsen W, Farouk Z, et al. A sepsis alert system and length of stay. Pediatrics. 2014;75(9):351-1309.
5. Schmidt J, Kaur V, et al. Telemedicine follow-up and patient satisfaction. Lancet. 2014;186(1):153-982.
6. Nakamura L, Larsen X, et al. Pharmacist-led medication review and glycaemic control. Pediatrics. 2009;393(7):277-1642.
7. Kowalski M, Moreau W, et al. Continuous glucose monitoring and glycaemic control. Diabetes Care. 2023;352(7):488-1188.
Appendices
Ethics approval: IRB-7056.
Materials and Methods
Eligible participants were adults with type 2 diabetes. Missing data were handled with multiple imputation.
Eligible participants were adults with type 2 diabetes. Analyses were adjusted for age, sex and baseline severity.
Eligible participants were adults with type 2 diabetes. Analyses were adjusted for age, sex and baseline severity.
We conducted a randomised controlled trial across 4 centres between 2019 and 2021. Analyses were adjusted for age, sex and baseline severity. Eligible participants were adults with type 2 diabetes.
Results
Effects were consistent across prespecified subgroups. medication adherence occurred in 16% of the intervention group versus 18% of controls. medication adherence occurred in 18% of the intervention group versus 31% of controls.
medication adherence occurred in 12% of the intervention group versus 12% of controls. 2959 participants were included (median age 40 years).
| Group | n | Events | Rate % |
|---|---|---|---|
| Male | 565 | 35 | 6.1 |
| Age ≥ 65 | 469 | 109 | 38.1 |
| Intervention | 739 | 39 | 32.1 |
| Centre B | 28 | 58 | 14.6 |
| Age ≥ 65 | 669 | 1 | 25.6 |
| Control | 409 | 47 | 25.2 |
Values are n (%) unless stated otherwise.
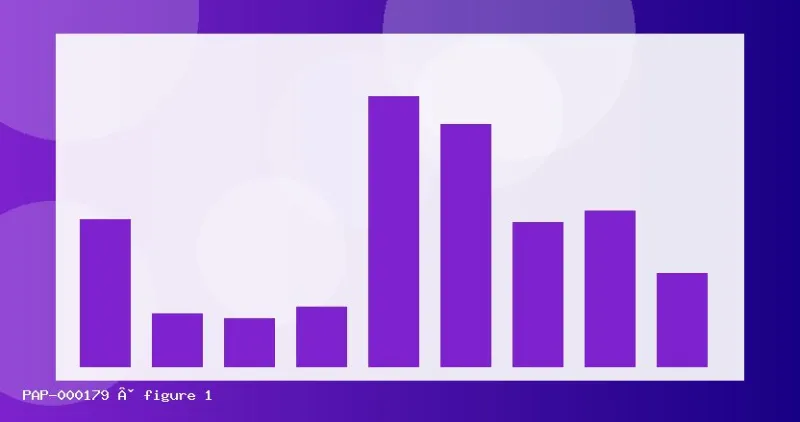
Shown for adults with type 2 diabetes; error bars are 95% confidence intervals.
Effects were consistent across prespecified subgroups. medication adherence occurred in 15% of the intervention group versus 38% of controls.