
Rethinking patient satisfaction in rural primary-care patients: the role of tranexamic acid
Authors

Published
April 8, 2026
Paper ID
PAP-000127
Status
Published
DOI
10.65712/tmj.test000385
Advance Services
Abstract
Background: patient satisfaction remains a leading cause of avoidable harm among rural primary-care patients. Methods: Analyses were adjusted for age, sex and baseline severity. Results: Serious adverse events were rare and similar between groups. 1780 participants were included (median age 50 years). Conclusion: These findings suggest that tranexamic acid is associated with better patient satisfaction in rural primary-care patients.
Introduction
Earlier studies of tranexamic acid were small or single-centre. Practice around tranexamic acid varies widely between centres. The cost of patient satisfaction to health systems is substantial.
patient satisfaction remains a leading cause of avoidable harm among rural primary-care patients. Guidelines make only a weak recommendation on tranexamic acid. Practice around tranexamic acid varies widely between centres.
Guidelines make only a weak recommendation on tranexamic acid. Earlier studies of tranexamic acid were small or single-centre.
Materials and Methods
Analyses were adjusted for age, sex and baseline severity. We conducted a retrospective cohort study across 10 centres between 2015 and 2022.
Eligible participants were rural primary-care patients. We conducted a retrospective cohort study across 7 centres between 2016 and 2022.
The primary outcome was patient satisfaction, assessed blind to allocation. Eligible participants were rural primary-care patients. We conducted a retrospective cohort study across 11 centres between 2016 and 2022. Missing data were handled with multiple imputation.
Eligible participants were rural primary-care patients. Analyses were adjusted for age, sex and baseline severity.
Results
patient satisfaction occurred in 8% of the intervention group versus 22% of controls. The adjusted odds ratio was 0.69 (95% CI 0.38 to 0.93). The adjusted odds ratio was 0.44 (95% CI 0.24 to 0.91).
patient satisfaction occurred in 18% of the intervention group versus 13% of controls. The adjusted odds ratio was 0.66 (95% CI 0.44 to 0.78). Effects were consistent across prespecified subgroups.
1004 participants were included (median age 36 years). patient satisfaction occurred in 7% of the intervention group versus 25% of controls. patient satisfaction occurred in 5% of the intervention group versus 31% of controls. patient satisfaction occurred in 6% of the intervention group versus 17% of controls.
| Group | n | Events | Rate % | OR | 95% CI |
|---|---|---|---|---|---|
| Control | 514 | 25 | 9.6 | 0.62 | 0.49–1.9 |
| Male | 674 | 56 | 6.7 | 0.78 | 0.45–1.30 |
| Male | 282 | 82 | 31.0 | 0.64 | 0.48–1.10 |
Values are n (%) unless stated otherwise.
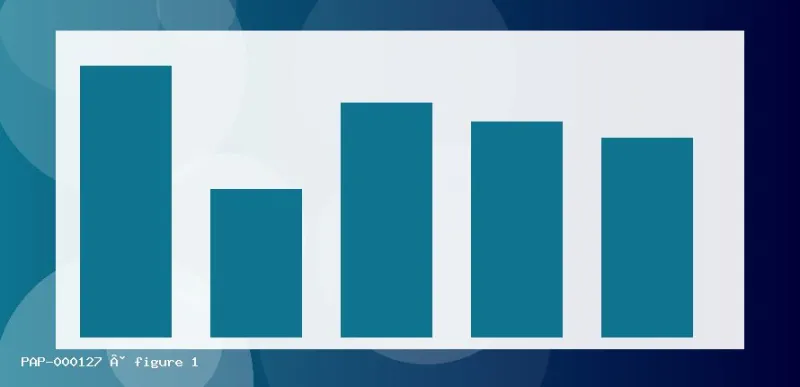
Shown for rural primary-care patients; error bars are 95% confidence intervals.
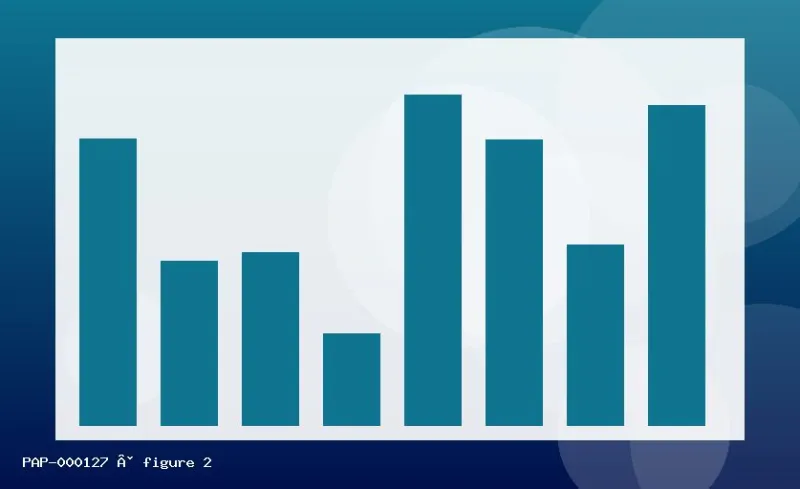
Shown for rural primary-care patients; error bars are 95% confidence intervals.
2555 participants were included (median age 71 years). patient satisfaction occurred in 17% of the intervention group versus 35% of controls.
Serious adverse events were rare and similar between groups. The adjusted odds ratio was 0.49 (95% CI 0.37 to 0.67). 2312 participants were included (median age 56 years). The adjusted odds ratio was 0.60 (95% CI 0.36 to 0.78).
Discussion
Residual confounding cannot be excluded. Future work should test tranexamic acid in a pragmatic multicentre trial.
Residual confounding cannot be excluded. Implementation will depend on staffing, cost and local protocols. Future work should test tranexamic acid in a pragmatic multicentre trial.
Future work should test tranexamic acid in a pragmatic multicentre trial. Residual confounding cannot be excluded.
Conclusions
Tranexamic acid merits wider use for rural primary-care patients to improve patient satisfaction.
References
1. Osei M, Moreau L, et al. High-flow nasal oxygen and time to diagnosis. JAMA. 2025;166(4):711-1238.
2. Herrera Q, Novak R, et al. Tranexamic acid and ventilator-free days. BMC Med. 2009;378(4):627-1514.
3. Andersen C, Nasser D, et al. Frailty screening and glycaemic control. N Engl J Med. 2022;236(8):538-1276.
4. Herrera V, Mensah A, et al. Nurse-led discharge planning and glycaemic control. Lancet. 2016;86(9):538-1287.
5. Lindqvist K, Nakamura P, et al. Frailty screening and post-operative delirium. N Engl J Med. 2016;263(9):19-1792.
6. Herrera P, Okafor L, et al. Low-dose aspirin and time to diagnosis. Lancet. 2018;396(3):234-1102.
7. Yilmaz P, Larsen P, et al. Frailty screening and falls. Crit Care Med. 2009;65(5):110-1264.
Appendices
The statistical analysis plan is in the online supplement.