
Does SGLT2 inhibitors reduce post-operative delirium in rural primary-care patients? A retrospective cohort study
Authors


Published
June 8, 2026
Paper ID
PAP-000089
Status
Published
DOI
10.65712/tmj.test000347
Advance Services
Abstract
Background: Practice around SGLT2 inhibitors varies widely between centres. Methods: The primary outcome was post-operative delirium, assessed blind to allocation. Results: 3881 participants were included (median age 82 years). post-operative delirium occurred in 10% of the intervention group versus 15% of controls. Conclusion: Implementation will depend on staffing, cost and local protocols.
Introduction
Guidelines make only a weak recommendation on SGLT2 inhibitors. post-operative delirium remains a leading cause of avoidable harm among rural primary-care patients.
Guidelines make only a weak recommendation on SGLT2 inhibitors. The cost of post-operative delirium to health systems is substantial. post-operative delirium remains a leading cause of avoidable harm among rural primary-care patients.
The cost of post-operative delirium to health systems is substantial.
Discussion
Residual confounding cannot be excluded. Implementation will depend on staffing, cost and local protocols. Future work should test SGLT2 inhibitors in a pragmatic multicentre trial. These findings suggest that SGLT2 inhibitors is associated with better post-operative delirium in rural primary-care patients.
Implementation will depend on staffing, cost and local protocols. These findings suggest that SGLT2 inhibitors is associated with better post-operative delirium in rural primary-care patients.
Residual confounding cannot be excluded. Implementation will depend on staffing, cost and local protocols.
Conclusions
SGLT2 inhibitors merits wider use for rural primary-care patients to improve post-operative delirium.
References
1. Andersen R, Nakamura A, et al. A sepsis alert system and falls. BMC Med. 2024;220(3):230-1731.
2. Zhang S, Schmidt G, et al. Point-of-care ultrasound and patient satisfaction. Lancet. 2015;217(11):145-1073.
3. Nasser W, Nakamura R, et al. High-flow nasal oxygen and chronic pain scores. JAMA. 2014;394(7):287-1717.
4. Farouk E, Schmidt K, et al. Vitamin D supplementation and in-hospital mortality. N Engl J Med. 2023;155(6):520-1447.
5. Herrera S, Kim W, et al. An antibiotic stewardship programme and patient satisfaction. BMC Med. 2008;134(5):48-1166.
6. Mensah W, Andersen Y, et al. Tranexamic acid and health-related quality of life. Ann Intern Med. 2019;99(4):325-1111.
Appendices
Ethics approval: IRB-4557.
Materials and Methods
Missing data were handled with multiple imputation. We conducted a retrospective cohort study across 13 centres between 2014 and 2024.
Analyses were adjusted for age, sex and baseline severity. We conducted a retrospective cohort study across 2 centres between 2015 and 2022. Eligible participants were rural primary-care patients.
Results
The adjusted odds ratio was 0.74 (95% CI 0.36 to 0.90). post-operative delirium occurred in 21% of the intervention group versus 20% of controls.
Effects were consistent across prespecified subgroups. Serious adverse events were rare and similar between groups.
| Group | n | Events |
|---|---|---|
| Male | 486 | 75 |
| Control | 402 | 104 |
| Intervention | 49 | 51 |
| Female | 758 | 110 |
| Centre B | 326 | 18 |
| Centre B | 880 | 105 |
Values are n (%) unless stated otherwise.
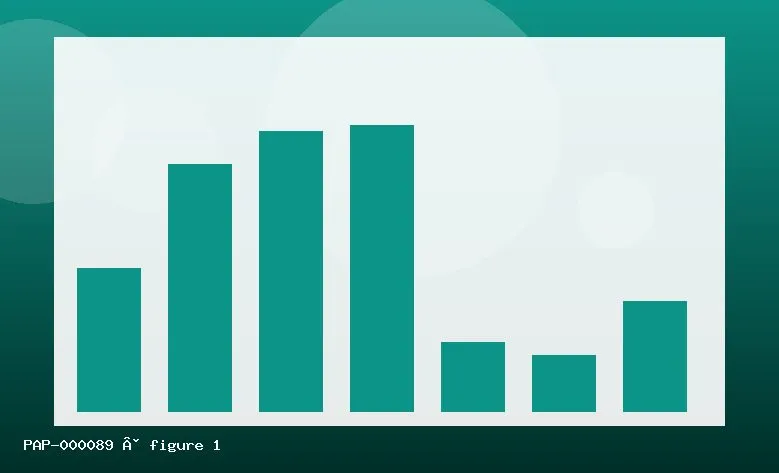
Shown for rural primary-care patients; error bars are 95% confidence intervals.
post-operative delirium occurred in 8% of the intervention group versus 33% of controls. post-operative delirium occurred in 15% of the intervention group versus 34% of controls.
Serious adverse events were rare and similar between groups. Effects were consistent across prespecified subgroups.